BREAKING: FOX NEWS STAR FACES UNEXPECTED HEALTH EMERGENCY — DETAILS STILL EMERGING
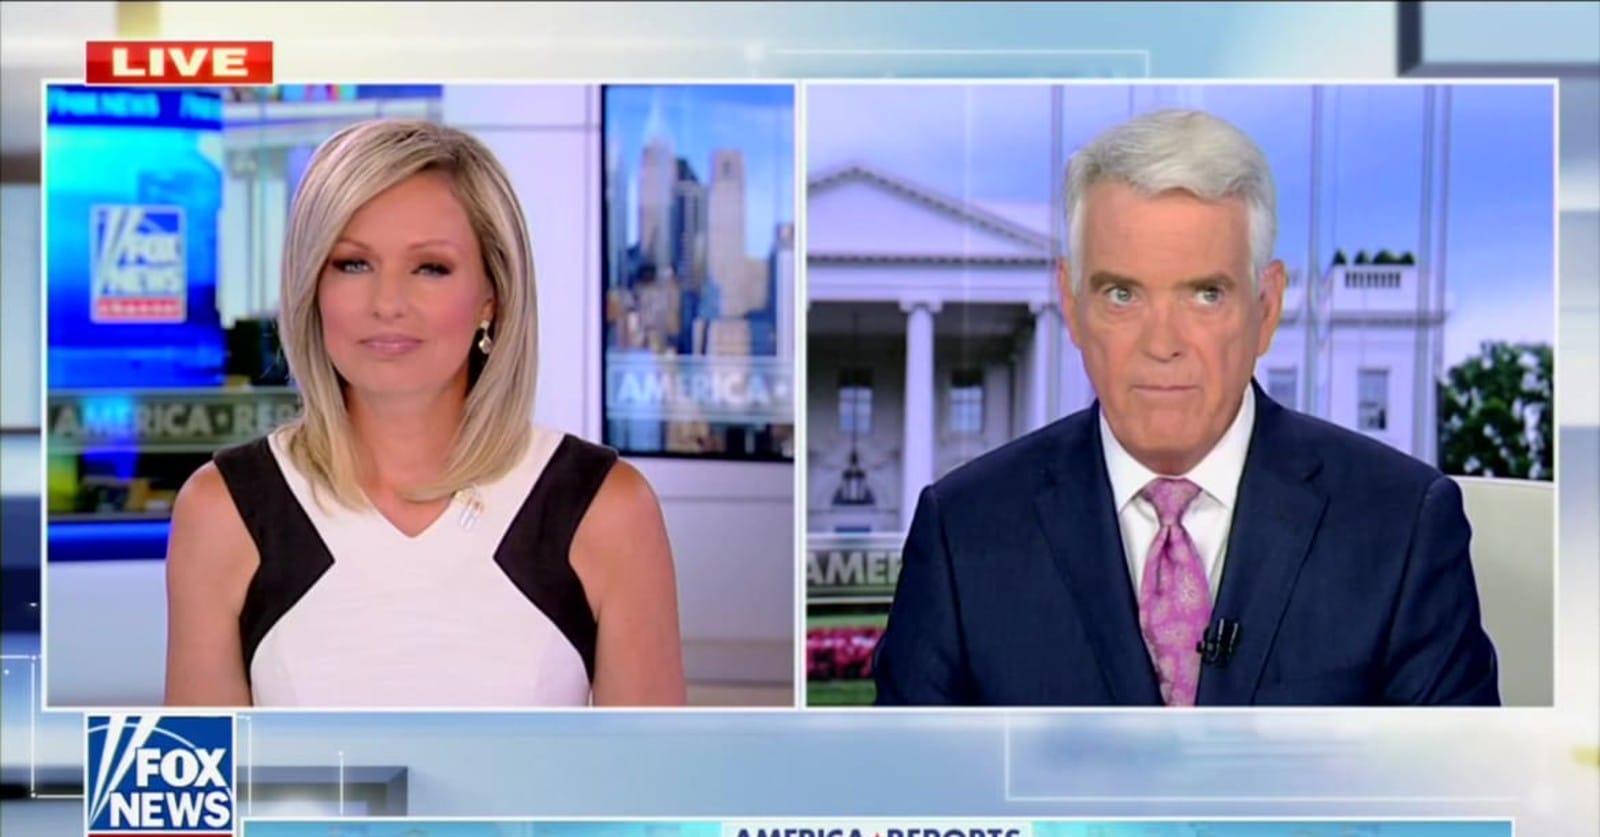
Fox News Anchor John Roberts Says Pericarditis Followed Two COVID Boosters—But His Broader Heart History Is More Complicated
Fox News anchor John Roberts has publicly connected two episodes of pericarditis to COVID-19 booster shots.
That disclosure is real.
During an August 10, 2026 segment of America Reports, Roberts said that after receiving a booster he developed pericarditis, the condition went away, and then it “came roaring back again” after a second booster.
He added that people can react differently depending on the individual.
The remarks quickly spread through conservative media and social platforms, where they were framed as a dramatic reversal from a journalist who had previously supported COVID vaccination.
There is a legitimate medical issue underneath the attention.
Myocarditis and pericarditis are recognized rare adverse events after COVID-19 vaccination, particularly after mRNA vaccines.
The Centers for Disease Control and Prevention says multiple vaccine-safety systems support a causal association between mRNA COVID-19 vaccines and myocarditis or pericarditis.
The Food and Drug Administration has required updated warnings in the prescribing information for Pfizer-BioNTech’s Comirnaty and Moderna’s Spikevax.
But Roberts’s personal history also demonstrates why one patient’s timeline should not be used to explain every later heart problem.
His public medical record includes cardiovascular disease that predates the booster account.
He had coronary stents before the pandemic-era booster controversy.
In early 2022, he was hospitalized after a previously implanted stent became blocked again and doctors also found an electrical conduction problem in his heart.
They reopened the stent and implanted a pacemaker.
Roberts later joked on air that he was now “battery powered.”
That 2022 hospitalization is well documented.
What is not established is that the hospitalization, the blocked stent or the need for the pacemaker was caused by a COVID vaccine.
Roberts himself had previously attributed his coronary artery disease in part to years of smoking.
The distinction is important because several different cardiac conditions appear in the story.
Pericarditis is inflammation of the thin sac surrounding the heart.
Coronary artery disease involves narrowing or blockage of the arteries that supply the heart muscle.
A pacemaker is generally used to treat certain abnormal heart rhythms or conduction problems.
Atrial fibrillation, or AFib, is another rhythm disorder in which the upper chambers of the heart beat irregularly.
Those conditions can coexist in one patient without having a single cause.
Roberts’s latest statement is specific.
He says the timing of his pericarditis tracked his booster doses.
He did not, in the quoted August segment, establish that every cardiac problem he has experienced was vaccine-caused.
That narrower claim is also more consistent with what health agencies actually recognize.
The CDC says myocarditis and pericarditis following COVID-19 vaccination are rare.
They have occurred most often in adolescent and young adult males, generally within a week after an mRNA dose, although cases have also occurred in women, older adults and after doses other than the second dose of the primary series.
Roberts, who is much older than the group in which the risk has been highest, would therefore not fit the most common demographic pattern.
That does not make his experience impossible.
It does mean his case should not be treated as representative of the average vaccine recipient.
The FDA’s updated 2025 labeling provides useful scale.
Using commercial insurance data for the 2023-24 mRNA vaccine formulation, the agency estimated an unadjusted incidence of myocarditis and/or pericarditis of approximately eight cases per million doses among people ages six months through 64 years during the first seven days after vaccination.
Among males ages 12 through 24, the estimate was about 27 cases per million doses.
Those numbers do not capture every formulation or every period of the vaccination campaign.
They do show why regulators describe the event as rare while still requiring a formal warning.
The FDA and CDC therefore occupy a position between two oversimplifications.
It would be wrong to say heart inflammation after COVID vaccination never happens.
It would also be wrong to say Roberts’s experience proves COVID vaccines commonly cause serious heart disease.
The evidence supports a rare, recognized risk whose magnitude varies substantially by age, sex, vaccine type and dose.
Roberts’s own account adds an individual case to that known safety issue.
It does not establish population-level risk by itself.
There is also an important question about additional doses after vaccine-associated heart inflammation.
Current CDC clinical guidance says development of myocarditis or pericarditis within three weeks after a COVID vaccine dose is a precaution to subsequent vaccination.
Additional doses should generally be avoided unless an individualized risk assessment supports proceeding after the episode has resolved.
That guidance reflects the fact that recurrence is a medically relevant concern.
Roberts says his pericarditis resolved and then returned after another booster.
Without access to his medical records, it is not possible to determine what advice he received, exactly when his symptoms began relative to each dose, which vaccine products he received, or whether clinicians formally classified each episode as vaccine-associated.
Those details matter medically.
The public has only his summary of the sequence.
That summary should be reported accurately without filling in missing information.
The timeline of his other heart problems is also important.
Roberts had coronary stents placed years before his 2022 pacemaker procedure.
When he returned to Fox News after that hospitalization, he said one of his existing stents had become blocked again and doctors reopened it.
He also said the “electrical circuitry” in his heart was failing, leading to the pacemaker implant.
Contemporary reporting did not describe that hospitalization as treatment for pericarditis.
That matters because later stories can unintentionally merge separate medical episodes.
A reader might see “pericarditis,” “hospitalized,” “pacemaker,” “AFib” and “COVID booster” in the same article and assume they were all parts of one vaccine injury.
The public evidence does not establish that.
Roberts later disclosed another rhythm problem.
In 2024, he wrote that he was being treated at the Cleveland Clinic for “intractable AFib” that had plagued him since what he called the whole “COVID thing.”
He eventually underwent an ablation procedure.
He later reported that he had gone a year without another AFib episode.
Again, his wording is broader than a direct vaccine-causation claim.
“The whole COVID thing” could encompass infection, vaccination, the pandemic period or some combination of those experiences.
Roberts has previously discussed long-COVID symptoms as well.
Without his medical records and his physicians’ assessments, the cause of his AFib cannot be established from that phrase.
COVID infection itself is also associated with cardiovascular complications.
CDC research has found that the risks of myocarditis and other cardiac complications after SARS-CoV-2 infection were higher than after mRNA vaccination in the populations studied during earlier phases of the pandemic.
That does not answer what happened to Roberts personally.
It is another reason his entire cardiovascular history cannot responsibly be assigned to one exposure based on timing alone.
The strongest evidence concerns the pericarditis episodes because Roberts himself explicitly linked them to the boosters.
Temporal association is meaningful.
A recurrence following another dose can make that association more clinically noteworthy.
But a personal statement is still different from a medical causality assessment.
Physicians assessing suspected vaccine-associated pericarditis typically consider timing, symptoms, electrocardiograms, inflammatory markers, imaging and alternative causes, including viral infections.
The CDC specifically advises clinicians to investigate other possible causes.
No such clinical documentation for Roberts has been made public.
His case therefore has two different levels of certainty.
At the first level, there is no real dispute about what Roberts says happened.
He says he developed pericarditis after one booster.
He says it resolved.
He says it returned after another booster.
Those are his own publicly recorded words.
At the second level is the medical explanation.
The known vaccine safety evidence makes his attribution biologically and epidemiologically plausible.
But outside observers do not have enough information to determine precisely how strongly his doctors attributed each episode to vaccination.
The same evidence does not support extending that attribution automatically to his blocked coronary stent, pacemaker or AFib.
This is also why the headline should be handled carefully.
Roberts was indeed hospitalized for a serious heart problem in early 2022.
He had a blocked stent treated and received a pacemaker.
But the available reporting does not show that the hospitalization was the pericarditis episode he discussed in August 2026.
Nor is there reliable evidence that he was airlifted to a hospital.
If “hospitalized after a health emergency” is intended to refer to the 2022 episode, that is accurate in broad terms.
If it is intended to say the vaccine-linked pericarditis directly caused that hospitalization and pacemaker procedure, the public evidence does not establish it.
Roberts’s comments are still significant because of his earlier position on vaccination.
In 2021, after criticism over a social-media post questioning vaccine effectiveness following the death of former Secretary of State Colin Powell, Roberts publicly rejected the suggestion that he was anti-vaccine.
He said he had been vaccinated, had participated in a public-service announcement encouraging vaccination and intended to receive a booster.
His new comments therefore document a change in his personal experience, not necessarily a reversal of the entire evidence base.
Someone can support vaccination and later experience a recognized adverse event.
Those two facts are not mutually exclusive.
Public-health communication is strongest when it can acknowledge both benefits and harms without treating either as forbidden information.
The existence of rare pericarditis after vaccination has been recognized by U.S. regulators for years.
The FDA has carried warnings since 2021 and strengthened the labeling with updated incidence information in 2025.
The CDC continues to advise clinicians to evaluate chest pain, shortness of breath or palpitations after vaccination and to report suspected cases.
That makes Roberts’s story medically relevant.
It does not make it a hidden side effect newly discovered in 2026.
Nor does his case show that regulators believe every subsequent cardiac condition in a vaccinated person was caused by vaccination.
The more defensible conclusion is narrower.
John Roberts has now publicly said that he developed pericarditis after a COVID booster and experienced a recurrence after another booster.
Pericarditis following COVID vaccination is a rare but recognized adverse event, with the highest observed risk in younger males.
Roberts also has a separate and complicated cardiovascular history involving coronary artery disease, a blocked stent, a pacemaker and atrial fibrillation.
Those conditions should not be collapsed into one causal story without medical evidence.
The most important unanswered questions are clinical ones.
Which vaccine products did Roberts receive?
How soon after each booster did the pericarditis begin?
How was each episode diagnosed?
Did his cardiologists formally classify the episodes as vaccine-associated?
And what relationship, if any, did they find between the pericarditis and his later rhythm problems?
Until those records or medical assessments become public, the factual boundary is clear.
May you like



Roberts’s account of recurrent pericarditis after boosters is real.
The broader claim that COVID vaccination caused all of his heart problems is not established.







